
Hello my dearest sissies, I do hope you are keeping very well indeed. On your knees this very instant, you filthy submissive whore. You are going to watch this video from the floor, is that quite clear, you little slut?
Do you feel like a sissy? Do you feel that feminine side of yours waking up little by little, the way it always does when a woman in a surgical mask tells you precisely what is going to be pushed into your body? Good. Keep it awake, because today Dr. Eve returns to the theatre for the second instalment of a procedure that no dignified man would ever consent to.
I expect your photographs in my inbox at hello@amarafetishclinic.digital, and I should very much like you to last the entire video without cumming in the first minute, you dirty sluts. Eight minutes and ten seconds, that is all, and I already know half of you will fail before the first instrument is even unwrapped.
Another film for you today, and this time we return to the Private-Patient klinik with Dr. Eve, who is without any question the star of that particular house. This is the second delivery of the urinary calculi series, and if you have not seen the first one, go back and watch it afterwards rather than pretending you have already done your homework.
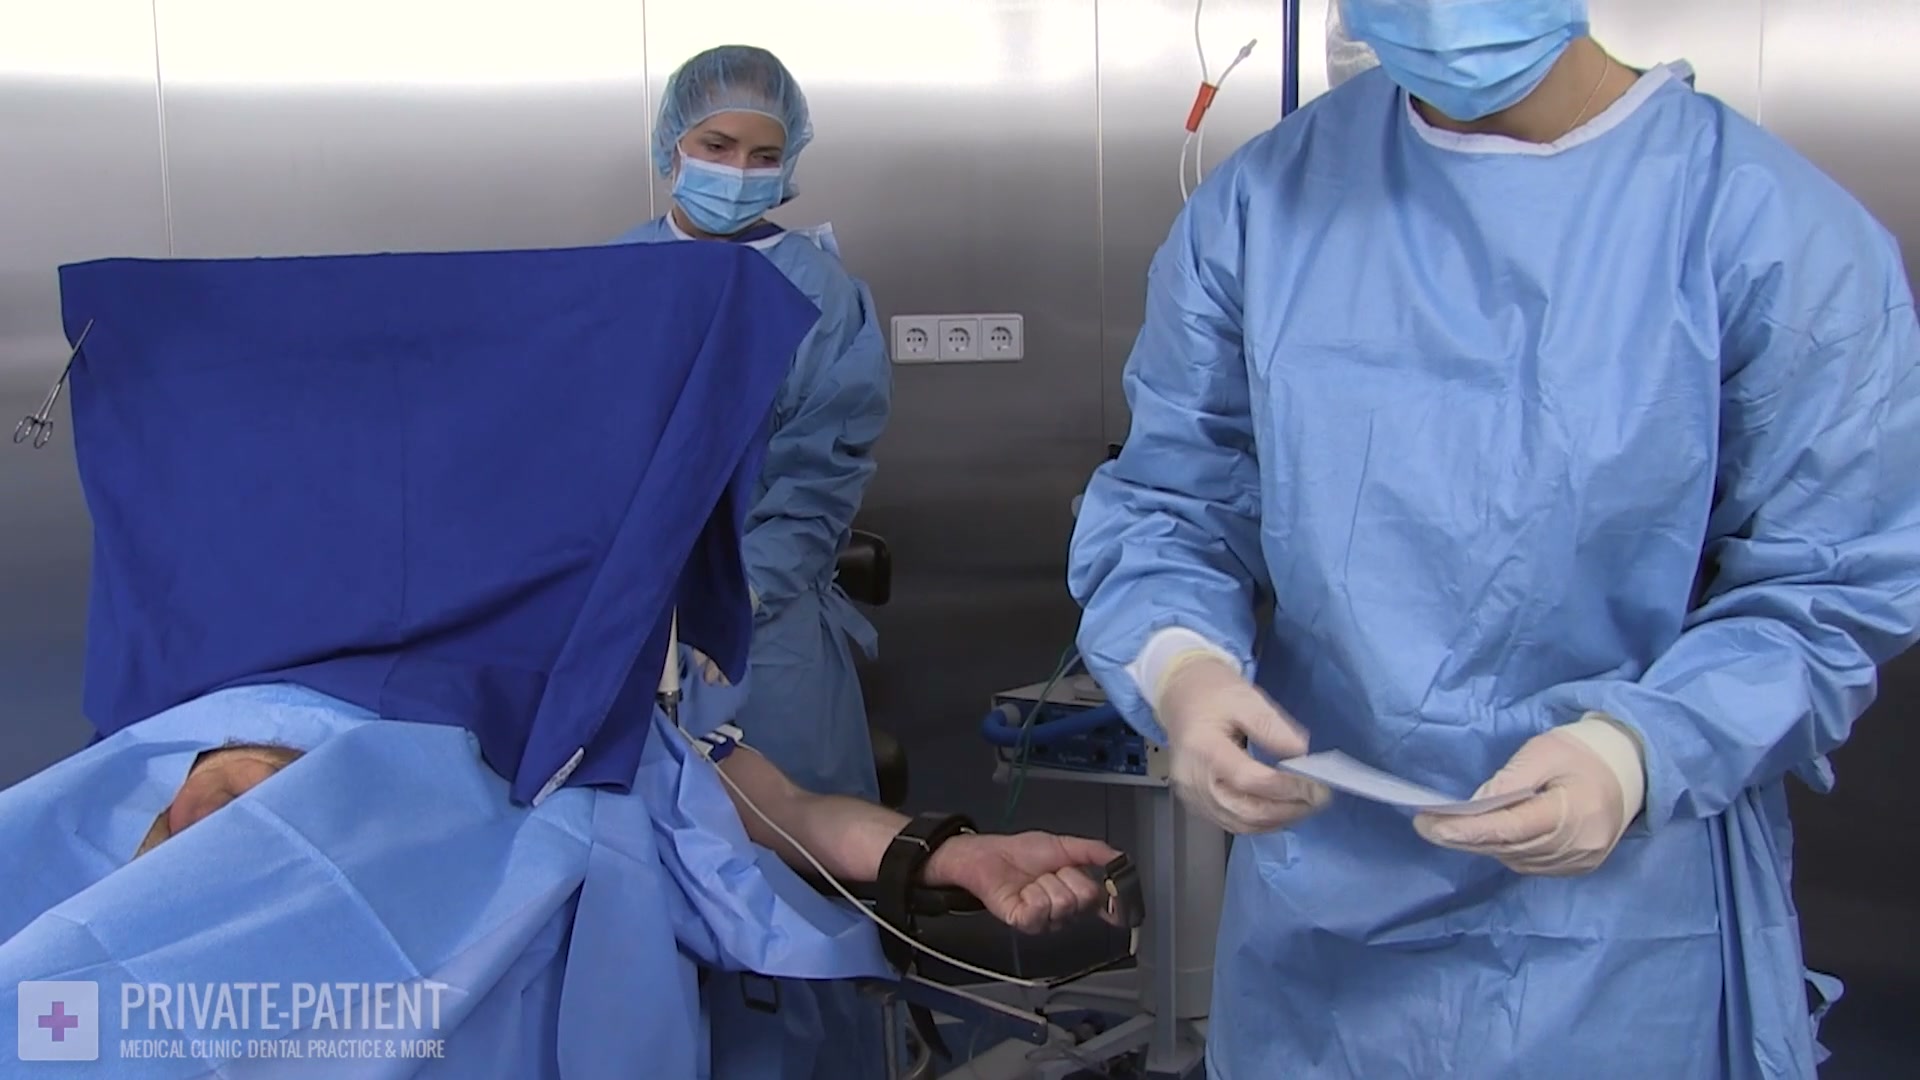
What you are looking at in the opening minute is a fully dressed theatre: stainless steel walls, blue drapes, a patient already positioned with one arm strapped to the table, and two women in scrubs who are entirely at ease in that room. The surgeon in the pale blue gown is unwrapping something small and sterile while the cap-and-mask nurse watches, and neither of them is in any hurry at all.
I am Mistress Katharina Amara, my legal name is Katia Van Looy, and I run the The Clinic (Private BDSM Medical Sanctuary) in Belgium. I review films like this one because Private Patient, bdsm productions of this standard are rare, and the ones that reach it understand that authority is built out of logistics rather than shouting.
Urinary calculi 02 and the discipline of a second visit
A second visit is always more interesting than a first, and any Dominatrix worth her gloves will tell you the same. On the first visit a patient is busy being frightened, which masks his personality. On the second he knows what is coming, and what arrives in his place is something far more revealing: anticipation, resistance, and the particular obedience of a man who has already tried to talk himself out of returning.
Dr. Eve understands this instinctively, and she plays the second appointment as what it is: a repetition with consequences. The patient is not greeted, he is processed. There is no small talk, no reassurance, no enquiry into how he has been since last time, because a private patient, medical bdsm and all the rest of it, exists in that room only as a body requiring a procedure.
For those of you who have never had the good fortune to be a numbered file rather than a person, let me explain what it feels like. It is restful, little sissy. Genuinely restful. When a woman has decided in advance exactly what is going to happen to you, the exhausting work of being an individual is taken off your hands entirely.
Private Patient bdsm and the question of authenticity
I am asked frequently whether Private Patient, bdsm filming of this kind achieves what it sets out to achieve, and my answer is honest rather than diplomatic. The staging is good, the equipment is real and the two women in this film are entirely convincing in their roles, which is more than can be said for most of what passes for clinical domination online.
Where it differs from my own work is in the aftermath. In a Private Patient klinik the camera stops when the procedure stops, and the patient is left to make his own sense of the afternoon. In my clinic the aftermath is the part I take most seriously, because a man who has been thoroughly handled needs somebody to tell him precisely what he was while he was being handled.
That conversation, the one that happens after the gloves come off, is the thing my regular patients remember longest. Read the Clinical Admission & Session Protocols if you want to know how it is structured, because I do not improvise it and I do not soften it for nervous applicants.
Private Patient fetish: why men watch and then book
The Private Patient fetish, as I have come to understand it from the letters in my inbox, is really a fetish for being on a list. Men who write to me about it are not primarily excited by instruments or by pain. They are excited by the idea of being expected somewhere, at a certain hour, by a woman who has written their name down and will notice if they do not appear.
That is a deeply unglamorous thing to admit, and I say it with affection rather than contempt. Half the men who visit this website are simply lonely and in need of a structure, and a clinical appointment supplies the structure with a precision that no other arrangement can match. There is a time, an address, a set of instructions and a woman who is entirely uninterested in negotiation.
If that description has made your chest feel tight, then you have understood your own condition better than you did five minutes ago. The route from there is not complicated: read, write, wait, arrive, obey. It begins at the contact page and it ends with you folded onto a couch in Belgium while somebody writes something unflattering about your composure.
The theatre as it appears in the frame
Look at the image at the top of this page again and count what is being communicated without a single line of dialogue. A patient under drapes with only a forearm exposed and restrained. A nurse standing at a distance that is respectful and clinical rather than warm. A surgeon who is looking at an instrument instead of at the man.
Every one of those choices says the same thing: this body is being worked on, not attended to. And that is the precise atmosphere that Private-Patient medical bdsm films manage better than most of their competitors, whether or not one approves of their approach to the patient's comfort, which I do not entirely.
The strapped arm deserves a particular note, because restraint in a clinical setting carries a specific erotic charge that no amount of leather can imitate. He is not tied because he is dangerous. He is strapped because a cannula needs to stay in place and because, quite frankly, it is easier for everybody if he cannot fidget about it.
Why the drape does more than any costume
A blue surgical drape is the most effective garment in this entire genre and it costs almost nothing. It conceals the body completely while advertising that the body has been opened, prepared and covered over by somebody with a plan. Nothing about the man beneath it remains his, and he cannot even see what is being done to him.
I use drapes in my own theatre for exactly this reason, and I recommend that any sissy who fantasises about a clinical session pays close attention to how it feels to be covered rather than exposed. Exposure is obvious. Draping is psychological, and the men who have experienced both tell me it is the covering, not the uncovering, that undoes them.
Watch how the nurse keeps her hands still throughout. She is not fidgeting with the drape, she is not adjusting it for the patient's comfort and she is not asking whether he is all right. Her stillness is a message from the whole room, and it is delivered without a word.
Catheterisation and the forgotten calculus
The word calculi means stones, which is to say mineral deposits forming where they have absolutely no business forming, and the treatment of them is a sequence of small indignities rather than one dramatic moment. That is why the film is titled after a diagnosis instead of after a procedure: the diagnosis is the whole story.
Any intervention that involves the urinary tract involves the placement of a catheter, and catheterisation, in the clinical sense, means a tube going somewhere a tube was never designed to go, while the patient lies still and is spoken to in the pleasant voice people reserve for difficult children. If you have never had it done, I suggest you imagine it and then write to me about what you imagined.
I have documented the practical side of this before in shaving the patient before inserting a urethral catheter and in Mistress Bedlam's catheterisation session, and both of those films show how much intimacy is produced by equipment that was never designed to be intimate.
What a private-patient klinik is for
A Private-Patient klinik, whatever the marketing suggests, exists to provide the one thing that a man cannot manufacture for himself: an authority that is entirely unimpressed by him. You can buy equipment online. You cannot buy the expression on the face of a woman who has done this two hundred times before.
That is why the films that work, including this one, never depend on shock. The theatre is tidy, the procedure is plausible, the women are calm and the patient is simply a patient. The eroticism is entirely in the ratio between how ordinary it all looks and how completely the man has surrendered his autonomy to two people in scrubs.
If you want the version with a Dominatrix who also happens to be a qualified nurse, the answer is on my Clinical Medical Team (Dominatrices & Nurses) page. If you want the version where the patient is reminded afterwards, at length, exactly how pathetic he looked under the drape, you will have to come to Belgium.
On Dr. Eve and the business of being a star
Dr. Eve is the star of Private-Patient and there is no point pretending otherwise, because she is the reason a large proportion of the letters I receive mention that site at all. There is something genuinely unsettling about a woman who can play a clinician without appearing to act, and Eve has that quality in abundance.
What I admire is the economy of her movement. She does not gesture for the camera, she does not deliver Asides to the audience and she never breaks character to check whether the shot is working. She simply proceeds, in the manner of a woman with a list of jobs and a limited amount of theatre time in which to complete them.
I have said before, in my review of the real truth about Dr. Eve, that a woman who plays a doctor properly is doing something considerably more difficult than playing a Dominatrix. Both roles require authority. Only one of them requires the specific coldness of somebody who has seen worse this week.
Nurse Shiva and the art of standing still
Nurse Shiva deserves more credit than an assistant usually receives, because standing still beside a procedure is a discipline in itself. She is not the one making decisions, she is the one whose presence tells the patient that decisions have already been made and that a second woman has agreed with them.
There is a lesson there for every sissy reading this. Two women in a room will always outrank one, and the silent one is usually more frightening, because her silence is not uncertainty but consent. When I work with a second Dominatrix the dynamic changes in exactly that way, and I have written about it in the check-up on Tessa.
Watch Shiva's eyes rather than her hands. She is watching the patient's face, which is what a properly trained theatre nurse does, and the patient knows she is watching. Being observed by somebody who is not going to intervene is a very particular form of helplessness, and it is underrated.
From their theatre to yours
You have watched eight minutes of somebody else being handled, little sissy, and somewhere in the middle of it the fantasy has quietly moved from him to you. That is exactly what this genre is for, and I have no intention of pretending that watching it constitutes any kind of achievement.
The men who get something out of this website and the men who simply consume it are separated by one action: the first group writes. Not a one-line demand, not a shopping list of services and certainly not a photograph of your cock sent without invitation, but a letter that describes who you are, what you want and what you are prepared to submit to in order to get it.
Everything you need is on the Clinical Admission & Session Protocols page, and I shall say the same thing I say to every applicant: read it twice, think about it overnight, and then write. Urgency is the mark of a man who has not thought this through, and unconsidered enquiries go straight into the bin.
The viewer's protocol
Kneel for the whole film with your hands behind your back and your eyes open. No touching, no edging, no clever excuses about how it does not count if you are wearing something. Eight minutes and ten seconds is nothing, and a man who cannot manage it on his own floor has no business discussing a three-hour appointment in a foreign country.
When it finishes, remain kneeling for five further minutes and think about the narrowness of that exposed forearm and the strapped wrist attached to it. Then write your report honestly, including the moment you nearly gave in, because that detail is worth more to me than any description of how hard you were.
Send it to hello@amarafetishclinic.digital with the subject line private patient two, attached to a photograph of you on the floor with your whole body in frame. I read all of them, and I remember the ones that are written properly.
Presenting yourself in Belgium
Everything you have watched this evening is preparation, and the standard it demonstrates is the standard you will meet at my clinic. Two women or one, a drape or a gown, a couch with stirrups and a patient who agreed to all of it in writing several weeks earlier: none of that is improvised.
A first appointment begins with a conversation about your limits, and that conversation is not a formality. I ask the same questions twice in different ways, I compare the answers, and I have turned away men who could not keep their story straight. A man who lies about his limits is a man who will lie about everything else when the gloves are on.
The full protocol, including preparation, dress, deposits and what is expected of a patient who has never been to a professional before, lives on our Clinical Admission & Session Protocols page. Bring your honest account of this film to your first appointment and I shall be considerably more interested in you than in the men who arrive claiming to have no limits at all.
Companions in the archive
No film of mine should be studied alone. Start with the first part of the urinary calculi series, because a second delivery without the first is only half the story, and then move to Patient Luva's first private-patient examination for the single-nurse version of the same theatre.
If you want the wider philosophy behind the drapes, the gloves and the numbering of patients, the bdsm medical archive explains it better than a paragraph can. And if your real ambition is to be examined properly under the protocol of a clinic rather than merely filmed, the sissy medical check-up is where a serious sissy begins.
The final word from Mistress Katharina
So here is my final word, my precious little sissies. Urinary Calculi 02 is a second visit, which means somebody signed up twice, and that is the only detail in this entire film worth admiring. Dr. Eve and Nurse Shiva do their work impeccably, but the courage, or the desperation, belongs to the man under the drape.
You have watched it, or you are about to, and the only thing separating you from him is a letter and a date in a diary. Write properly through the contact page, arrive on time, hand over your dignity at the door and discover how extraordinarily light a man feels once two women in gloves have decided exactly what happens next.
Theatre lights are on, the drape is folded, the trolley is laid and Mistress Katharina Amara is waiting to see whether a sissy like you is genuinely ready to be handled, or merely fond of watching other men be.
