
Hello my dearest sissies, I do hope you are keeping very well indeed. On your knees this very instant, you filthy submissive whore. You are going to watch this video from the floor, is that quite clear, you little slut?
Do you feel like a sissy? Do you feel that feminine side of yours waking up little by little, the way it always does when a woman in a surgical mask tells you precisely what is about to happen to the body in front of her? Good. Keep it awake, because today I am not merely examining a man. Today I am bringing one back from the dead.
I expect your photographs in my inbox at hello@amarafetishclinic.digital, and I should very much like you to last the entire video without cumming in the first minute, you dirty sluts. Thirteen minutes and fifty-three seconds, that is the sentence, and half of you will spill in the first two like the pathetic, dripping little things you are.
Here is another film from my own collection, and this one is rather more proper than the last. It is a resuscitation scene involving intubation, and yes, that is exactly what it says on the label. I am Dr. Amara, a resident physician in cardiology, and the man on the trolley in front of me is in cardiorespiratory arrest, which means, in plain English for the slower sissies, that his heart has stopped and he is no longer producing a cardiac frequency of any kind.
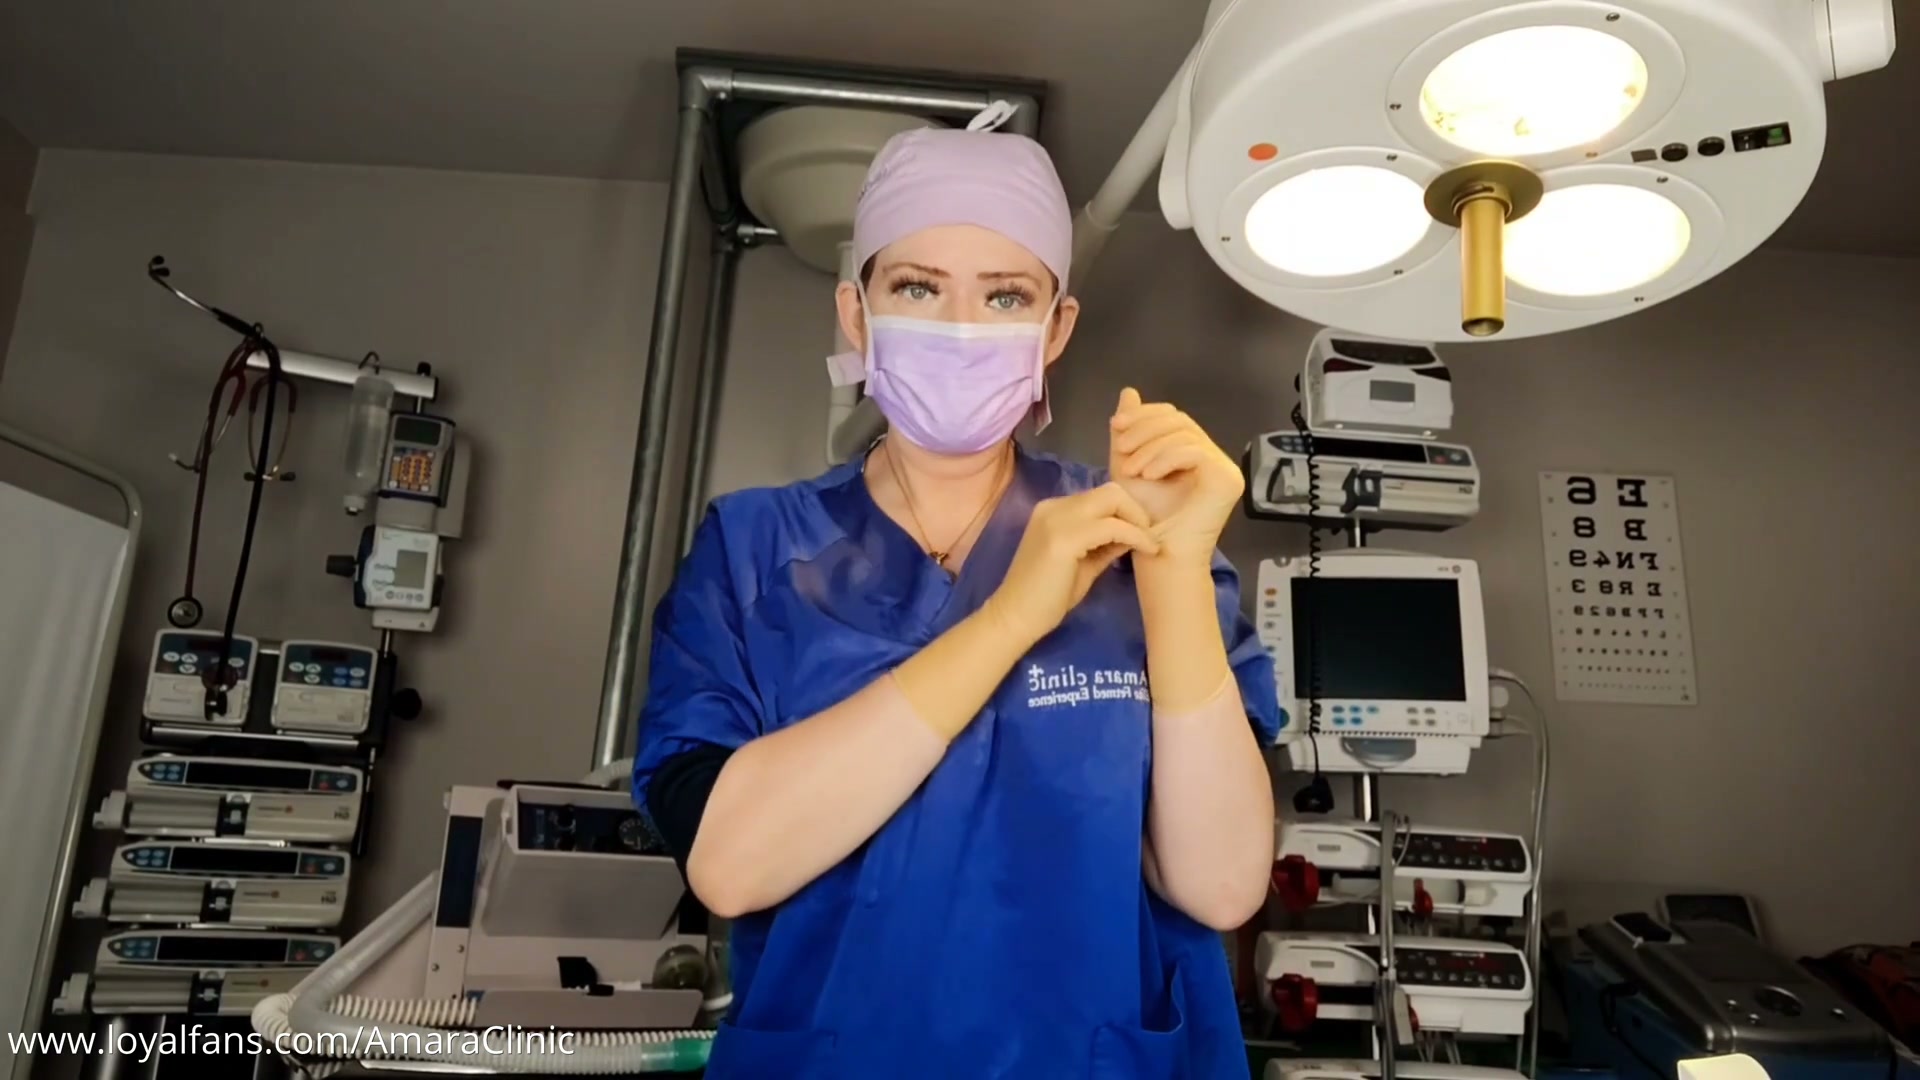
Watch the opening seconds with your eyes open. Purple cap, mask over my mouth, blue scrubs, and two gloved hands being pulled on with the small, practised snap that tells you the woman doing it has done it ten thousand times before. Behind me the theatre lights are burning, the monitors are stacked and humming, and the tube I am going to slide into that man's throat is already prepared. Everything in this frame is a promise, little sissy, and I always keep my promises.
My name is Mistress Katharina Amara, my legal name is Katia Van Looy, and I run the The Clinic (Private BDSM Medical Sanctuary) in Belgium. I am a qualified nurse, I have stood at the business end of real emergencies, and I have long since stopped finding it strange that the most powerful thing a man can give me is his body while it is completely out of his control.
A cardiac arrest in my emergency department
Our patient arrived coding. There is no elegant way to describe it, and elegance is not what the first minutes of a resuscitation are for. First I take the airway and assess, then I begin manual resuscitation with my own hands, because the heart of a man who has stopped being interesting to anybody else still needs somebody to push for him.
This is where a great many of you would fail, incidentally. Not from weakness of the arms, but from weakness of the mind. A resuscitation is rhythm, patience and utter absence of panic, and any man who cannot hold a position for thirteen minutes without fidgeting has no business imagining himself in my theatre. The clinical admission desk is full of men who overestimate their own stamina, and I take a particular pleasure in correcting them.
What I want you to notice as you watch is how little I emote. There is no shouting, no drama, no flapping of hands. My voice stays level, my instructions stay short, my gloves stay clean and my eyes never leave the patient. That stillness is the most frightening thing in the room, little slut, because it tells everyone present that I am entirely in command of a situation the patient has no say in whatsoever.
Why the heart stops being polite
A heart is a muscle that obeys instructions from above, and when those instructions fail, the whole arrangement collapses with astonishing speed. One moment a man is a person with opinions and a telephone and a diary. A few seconds later he is a chest that requires compression and a mouth that requires a tube, and none of his opinions are of the slightest use to anyone.
I find that transition endlessly erotic, and I refuse to apologise for saying so on my own website. The fantasy that brings so many men to this clinic is precisely this: to be reduced, thoroughly and clinically, to a body that another woman handles according to protocol. The resuscitation scene is the purest expression of that fantasy I have ever filmed.
It is also, I ought to add for the nervous ones, a completely controlled piece of theatre inside a genuinely competent framework. I know precisely what I am doing at every second, my limits are written down before anybody lies on that trolley, and the equipment is real. Safety, you see, is what allows the cruelty to be so complete.
Manual compressions first, always
Before any sophisticated intervention, there is the heel of a hand on a sternum and a rhythm that must not break. Compressions come first because nothing else matters until circulation is restored, and I make a point of beginning every resuscitation scene this way, with the physical work and the physical contact, because that is what makes the audience believe it.
You will hear my gloves against his skin, and you will hear the trolley answering with a small metallic complaint every time the pressure goes down. It is an intensely physical sequence and it is the part men write to me about afterwards, often in surprising detail, usually with the admission that they had never before considered how helpless a grown man looks with his chest being driven by somebody else's arm.
And when the rhythm settles, when my shoulders find the stroke and the count, the theatre becomes very quiet apart from the monitors. That is the moment I enjoy most. Not the noise of an emergency, but the silence of a room entirely organised around my hands.
Mistress Katharina Amara bitch and other words men type at night
I am told this is the phrase a good many of you use to find me, typed at some ungodly hour with one hand occupied elsewhere and the other barely keeping up. Mistress Katharina Amara bitch. Well. I have been called far worse by far better men, and I am not so delicate that a crude noun keeps me awake at night. Since you are here, however, let us be accurate about what the word actually describes.
I am a bitch in the only sense that carries any weight: a woman who does exactly what she said she would do, on the schedule she announced, regardless of how much the man in front of her whimpers about it. The word is not an insult in my house. It is a job description, and the men who use it as one are the men who come back year after year.
So if you arrived here looking for a woman to be unkind to you with genuine competence, you have found her, and you may stop pretending you were searching for something else. Begin properly through the Clinical Admission & Session Protocols page, read it twice, and write to me in complete sentences. Sloppy enquiries receive sloppy silence.
What a bitch in blue scrubs actually does
She arrives early and checks her equipment before the patient is even undressed. She says the same words to every man in the same tone, so that nobody can claim he was treated unfairly. She keeps the theatre cold, the light direct and the conversation entirely one-sided, because a patient who is talked at cannot start negotiating.
Then she takes a man who believes himself to be reasonably composed and reduces him to a chest and an airway, and she does it without raising her voice once. That reduction is the service. It is also, and I say this with the full weight of a nurse's experience, remarkably good for him, because a man who has been properly handled stops pretending to be a man entirely.
I have written about this dynamic in the resident cardiologist and the coding patient, where the same theatre and the same monitors appear and the same obedience is extracted, and I shall keep writing about it as long as men keep arriving at my door believing that they are the ones in control.
The discipline behind the theatre lights
Every light above that trolley is there because a real clinician needed it, and every monitor is switched on because I do not, under any circumstances, perform a clinical scene with dead equipment. If a man is going to be reduced, he deserves to be reduced inside an authentic environment, and authenticity is expensive, exhausting and absolutely non-negotiable.
That is why I invite nervous applicants to look carefully at the rooms on the The Clinic (Private BDSM Medical Sanctuary) page before they write. Not one item in this film is a prop bought for a photograph. The surgical lights hang where they hang for a reason, and the cables on the wall are connected to machines that make noise.
Discipline, in the end, is not shouting at people. It is the accumulation of a thousand decisions taken correctly before the patient ever arrives, and any Dominatrix who has not done that work is merely an actress with a stethoscope. I have met a fair few of those, and I have written about several of them on this blog without any particular charity.
Intubation, step by step
Once circulation has been addressed, the airway becomes the whole world. Intubation is not simply pushing a tube down a throat, whatever the more excitable corners of the internet may suggest. It is positioning, visualisation, control and confirmation, and each of those stages takes place while the patient has absolutely no say in what is being done to him.
I begin with the head. The neck is extended, the jaw is lifted, the alignment is checked, and I take my time over it because a badly positioned head makes everything that follows both unsafe and unconvincing. My gloved fingers move over a jawline and throat the way a collector handles something valuable, and I have had patients tell me that this was the moment they stopped thinking entirely.
Then the laryngoscope is introduced, the blade is placed, the anatomy is gently persuaded into view, and the room contracts to the small illuminated space at the end of my instrument. There is a particular silence in a theatre at that moment, and in this film you can hear it. It is the silence of a man's entire existence being reduced to whether a woman can see the opening she needs.
Positioning the head, owning the airway
Men underestimate how intimate an airway is. A mouth that is being held open by an instrument, a tongue that has been moved aside and a throat that is being entered by something that is not a cock are three separate humiliations arriving at the same time, and the body reacts to all of them at once.
In my clinic the mouth is examined as carefully as everything else, which is why the maxillofacial trauma induction film sits in the same archive as this one. The principle is identical: a woman who owns the airway owns the man, and he can feel the ownership in his teeth.
You will notice that I speak to him throughout. Not soothingly, and certainly not flirtatiously. I tell him what I am doing, in the flat tone of somebody reading out a list, because the sound of a woman describing her own actions while performing them is the most complete form of dominance I know.
The tube, the laryngoscope and the silence
The tube goes in with a precision that looks effortless and is not. Once it is placed, the cuff is inflated, the position is confirmed and the circuit is connected, and at that point the patient's breathing belongs to my equipment rather than to his body. I want you to sit with that thought for a moment, little sissy, because it is the heart of the whole film.
From this moment on, every breath the man takes is a decision I have made on his behalf. Not a metaphor, not a roleplay flourish, but a literal arrangement of tubes and pressures, and there is no more honest demonstration of what submission means. He is not breathing for me. He is being breathed for, and the difference is everything.
Afterwards, when the scene ends and the equipment is cleaned down, I always spend a few minutes in the theatre alone. I like the smell of it, the cold of it, and the knowledge that a room which terrified a grown man an hour earlier is now completely silent and waiting for the next one.
What I write in the notes
Every scene, real or performed, produces notes, and my notes are written by hand and kept. Time of arrival, presenting condition, the sequence of interventions, the response of the patient, and a short, unflattering assessment of his composure. My handwriting has been described by a patient as the most frightening document he had ever been shown, and he was a solicitor.
Those notes serve a clinical purpose first and a sadistic one second. They let me remember, months later, exactly how a man behaved when he was genuinely out of his depth, which is information no conversation will ever give me. They also let me greet a returning patient with the single detail he hoped I had forgotten.
If you find that idea unbearable, you are not ready. If you find it unbearable and you cannot stop thinking about it, then you are exactly the sort of perverted little creature this clinic was built for, and you should probably read the protocols tonight rather than next year.
Cardiology is a fetish of control
People assume that the erotic charge in a medical fetish scene lies in the instruments. It does not. It lies in monitoring, and cardiology is the most monitoring-obsessed specialty in the whole hospital. A heart is watched, traced, counted and alarmed, and a patient attached to that apparatus cannot hide a single thing about how he feels.
That is why I love this character, and why I keep returning to her. As Dr. Amara, resident physician in cardiology, I am the woman who reads the truth off a screen while the man on the trolley attempts to lie to me with his face. The monitor always wins, little sissy, and I have never once been fooled by a brave expression.
The films in this category are, I am aware, closer to theatre than to pornography in places, and I make no apology for that either. A woman taking total control of a man's body on camera needs no gratuitous nudity to be filthy. The filth is in the authority, and authority, properly performed, is the most explicit thing there is.
The monitor as a collar
Attach a man to a monitor and you have collared him more effectively than any leather in my cupboard. He cannot move without the trace changing, he cannot hide his arousal, and he cannot pretend that the woman watching the screen does not know exactly what is happening inside his chest. It is surveillance as foreplay, and it works on the most stubborn men.
I have had patients arrive convinced that they were going to remain composed and detached throughout a clinical session. Within four minutes of being wired up and told to lie still, they are sweating, apologising and answering questions far more honestly than they intended. The machine does my interrogating for me, and I simply stand there looking unimpressed.
If that thought makes your cock twitch while your stomach drops, then you have understood the appeal of this entire website. That contradiction is the product, little slut. Nobody books a session with me hoping to feel calm and reasonable, and the ones who claim otherwise are lying to themselves in a way I find almost charming.
How to watch a fourteen-minute resuscitation
This film is longer than the last one, which means I expect rather more of you. Thirteen minutes and fifty-three seconds on your knees is a genuine test for a man who has spent years watching this sort of material collapsed in a chair, and I want you to fail it properly rather than cheat it discreetly.
Kneel with your back straight, your hands behind your back and your eyes on the screen. No cushions, no leaning, no propping yourself against the sofa. If your knees begin to complain in the fourth minute, they are meant to, and you will remain exactly where you are until I am finished with you, which is the whole point of the exercise.
Somewhere around the middle of the film you will notice that you have stopped thinking in sentences. That is the correct response and it is the reason I make these videos as long as I do. A two-minute clip produces an erection, a fourteen-minute clip produces a state of mind, and it is the state of mind I am after.
The kneeling protocol
Before you press play, put your telephone face down and out of reach, because a sissy who checks notifications during my resuscitation scene is a sissy who has understood nothing. Then set a timer, because I shall ask you in your report how long you genuinely held the position and I am extremely good at spotting a rounded number.
When the film ends, do not stand up immediately. Remain kneeling for five further minutes in silence and let the whole thing settle into you. Then write your report by hand or by keyboard, whichever produces the more honest sentences, and include the moment at which you nearly gave in, because that detail interests me far more than any description of your cock.
Send the report, your photograph and your honest numbers to hello@amarafetishclinic.digital with the subject line resuscitation. I read every one personally, and I have been known to reply to the good ones within a day, which is more attention than most of you are given by anybody else in your lives.
Presenting yourself at the clinic
Everything you have watched is preparation. The film is the demonstration, the kneeling is the rehearsal and the report is the audition, and none of it becomes real until a man puts himself through the door of a clinic in Belgium and discovers that the theatre is colder than it looks on a screen.
My Clinical Medical Team (Dominatrices & Nurses) works to precisely the standards you have seen here, and every one of them has been trained by me in the handling of nervous men in clinical environments. You are not obliged to begin with me personally. You are obliged to begin properly, which means a written enquiry, an honest description of your limits and no theatrical bravado in the first paragraph.
The full protocol, including preparation, dress, deposits and what happens when a patient fails to follow instructions, is set out on our Clinical Admission & Session Protocols page. Read it sitting up, at a desk, like an adult, and do not write to me until you have finished it. I can always tell when a man has skimmed, because his first question is answered in the second paragraph of the page he ignored.
Companions in the archive
No film of mine should be studied alone. After this resuscitation, watch the anaesthesiology induction POV for the same theatre seen from the patient's own eyes, and then our patient is coding for the emergency that precedes everything you have just watched.
If you want the wider philosophy behind the gloves, the monitors and the voice, the bdsm medical archive will explain it better than I can in a paragraph. And if your taste runs to the more humiliating end of clinical discipline, the examination that goes wrong will show you what happens when the equipment stops being cooperative and the woman in charge refuses to panic.
The final word from Mistress Katharina
So here is my final word, my precious little sissies. This is a resuscitation scene involving intubation, performed by Dr. Amara, resident physician in cardiology, and it is the most complete demonstration of clinical ownership I have ever put on film. A man stops breathing, a woman takes over, and nothing in that theatre moves without her permission.
You have watched it or you are about to, and the only difference between you and the patient on that trolley is a letter and a date. He stopped being nothing the day he knelt for me. You can keep drifting through your grey little weeks pretending that the monitor is not watching, or you can write to me through the contact page and be examined, documented, disciplined and owned.
The lights are on, the gloves are on the trolley, the tube is prepared and Mistress Katharina Amara is already unimpressed by whatever excuse you were about to make. Kneel, breathe, obey, and discover how much lighter a man feels once a woman has taken absolutely everything off his hands.
